
Some things should not wait for the next free routine appointment. Some things should not wait for the next free routine appointment. Telephone the practice and say what is happening, or go to an emergency room, if you have a mole or a mark that has changed shape, colour or size, that has become raised or uneven, or that bleeds, itches or will not heal; a sore anywhere that has not healed in three weeks; a rash that is spreading quickly, especially with fever, blistering, or peeling skin; a painful rash in a band on one side of the body, particularly near an eye; redness that is hot, swollen, tender and spreading, which can be a deep skin infection; a new rash after starting a medicine, especially with mouth or eye involvement; or a child under three months with any widespread rash. If you have been treated here and something is worse rather than better after a procedure, telephone us rather than waiting for the review appointment. We would far rather field a call that turns out to be nothing.
Basal cell carcinoma is the commonest cancer in humans. It grows slowly, it very rarely spreads elsewhere in the body, and left alone it keeps growing locally and destroys what is in its way — which on a face is the entire problem. It typically appears as a small pearly or translucent bump with fine vessels visible across it, or as a flat scaly patch, and characteristically it bleeds, scabs, seems to heal and then does it again.
Squamous cell carcinoma is the second commonest. It tends to be scaly, crusted, sometimes tender, sometimes growing quickly, and it usually appears on the parts of the body with the most cumulative sun exposure — the face, the ears, the scalp on a bald head, the lips, the forearms and the backs of the hands. Unlike basal cell, it can spread, which is uncommon but is why it is treated with more urgency and why the ear and the lip are watched more carefully than the forearm.
The practical message for both is the same and it is the three-week rule: a sore anywhere that has not healed within three weeks needs looking at. Almost everybody who arrives with a large one explains that they thought it was a scratch, a shaving cut, a spot or an insect bite, and that it kept nearly healing. Nearly healing and then breaking down again is the characteristic behaviour, not evidence against it.
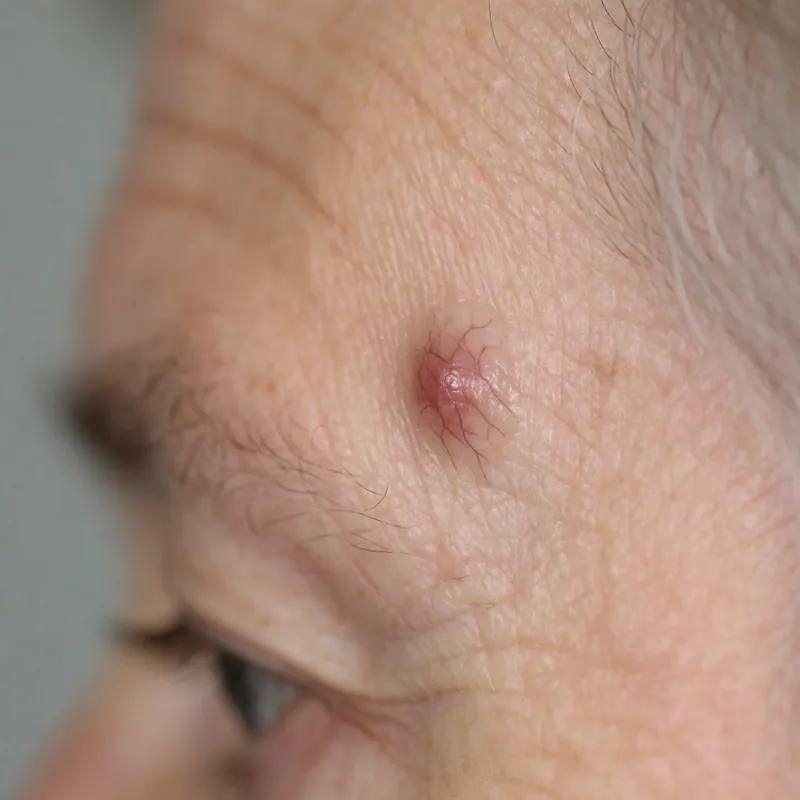
How they usually present
Descriptions to prompt an appointment. Nothing here allows you to identify or exclude anything on yourself.
A pearly bump with visible fine vessels
Often on the nose, the cheek, the forehead or the ear. Small, shiny, sometimes with a rolled edge and a dip in the middle. It may bleed after washing or shaving and then crust over.
A sore that will not heal
Three weeks is the threshold worth remembering. A patch that scabs, sheds, bleeds a little and scabs again over months is the presentation that gets ignored for longest.
A flat scaly patch that is slowly widening
Frequently on the trunk, often mistaken for eczema or a fungal patch, and often treated with a cream for a year before anybody examines it properly. A patch that does not respond to treatment for what it was assumed to be is itself a reason to reassess the diagnosis.
A firm scaly or crusted lump, sometimes tender
More typical of squamous cell, more likely on sun-exposed sites, and sometimes growing over weeks. Tenderness is a feature worth mentioning because it is comparatively unusual in harmless growths.
A rough patch that keeps returning after being frozen
Sun-damage patches are common and treatable — see /actinic-keratosis.html — but one that keeps coming back in exactly the same place, or becomes thick or tender, is the one that gets sampled rather than frozen again.
How they are treated
The choice depends on which cancer it is, how big, how deep, where on the body, and on you.
Excision with a margin
The standard treatment for most: the lesion and a rim of normal skin around it, removed under local anaesthetic and closed with sutures. The specimen goes to the laboratory, which confirms the diagnosis and confirms that the margins are clear. Most take under an hour. See /skin-cancer-surgery.html.
Curettage and electrosurgery
Scraping the lesion away and sealing the base with a fine current, appropriate for certain low-risk basal cell cancers in the right place. It heals as a flat pale circle rather than a line and is quicker, but it produces no margin for the laboratory to assess, so it is only used where that is an acceptable trade.
Topical treatment, in selected superficial cases
Some very superficial basal cell cancers can be treated with a prescription cream used at home for several weeks. It works by provoking a substantial inflammatory reaction, so the treated area looks considerably worse before it looks better, and people stop early unless that is explained beforehand. It is not appropriate for anything thick, recurrent or on a high-risk site.
Staged surgery elsewhere, for the difficult sites
Cancers on the eyelid, the lip margin, the nose tip, the ear cartilage, anything recurrent, and certain aggressive growth patterns are referred for staged microscopic surgery, where margins are checked while the patient waits and the reconstruction is planned. That is not done here and we refer it rather than attempt it.
Radiotherapy, occasionally
For patients in whom surgery is not sensible, or for particular sites. It is arranged through the referral rather than provided here.
Afterwards
What follow-up actually consists of, and why it lasts.
The wound
Sutures out in five to fourteen days depending on the site. Keep it dry for forty-eight hours, then clean and re-dress as instructed. Some bruising and tightness is normal; spreading redness, heat and increasing pain from day three onwards is how an infection announces itself and is a reason to telephone.
The scar
It will be visible. A line on the face usually settles to something pale and inconspicuous over six to twelve months, but it takes that long, and it is red and firm in the middle of that period. On the chest, shoulders and jawline scars are more likely to thicken, and if that applies to you we will have said so beforehand.
The result
You are telephoned with the pathology report, including confirmation that the margins were clear. If they were not, a further procedure is arranged, which is a normal outcome rather than a failure — some of these have a wider footprint under the surface than on it.
Regular skin examinations from then on
Having had one is the strongest predictor of having another, and a meaningful proportion of people develop a second within a few years. Follow-up is usually annual and sometimes more frequent, and it examines all of your skin rather than only the scar.
Sun protection, which is now genuinely preventive
This is the one point on this page where daily sunscreen, sleeves, a hat and shade actually change what happens to you next. See /sun-protection.html, which names no products.
Basal & Squamous Cell Cancer in western Queens
The two common skin cancers. Both are usually slow, both are usually cured by removing them, and both are routinely ignored for a year because they look like a sore that will not heal. Most are treated in this building.
Every appointment here starts the same way: a proper history, an examination in good light, and a named diagnosis said out loud and written down for you to take home. If there is genuine doubt you will be told that, and told what would settle it — usually a biopsy. You leave with a plan that has a strength, a site, a frequency and a date to stop or come back on it, and, where the condition is one that relapses, what to do on the first day of the next flare. If the honest answer is that this is better left alone, or that it belongs somewhere other than here, that is what you get instead, and it costs exactly the same.
This page is not medical advice, and it is not a diagnosis. Nothing on this website is medical advice for you in particular, and it is not a diagnosis. These pages describe conditions in general terms so that you arrive knowing what the questions are — they cannot tell you which condition you have, because that requires somebody to look at your skin, feel it, ask you a hundred questions and frequently take a sample of it. Two conditions on this website can look identical in a photograph and need opposite treatments. If something on your skin is new, changing, painful or not healing, the useful next step is an appointment rather than more reading.
No before-and-after photographs, and no promised outcome. There are no before-and-after photographs on this website and there never will be. Every set you have seen somewhere else was chosen from a much larger pile, and the second picture is usually taken in different light, at a different angle, at a different point in a flare cycle. In dermatology the dishonesty is sharper than in most fields, because nearly every condition here fluctuates on its own — photograph any relapsing skin disease at its worst and again at its best and you have a persuasive pair of images that demonstrates nothing about the treatment in between. What we publish instead is what a treatment typically achieves, in how long, in what proportion of people, and how often it does not work.
The risks, plainly. Every treatment described here has side effects, and some carry real risks. Topical steroids thin skin if they are used at the wrong strength on the wrong site for too long, which is why they are prescribed with a site, a strength and a stopping point rather than handed over indefinitely. Light-based and laser treatment can burn, blister and cause pigment change that lasts months, and that risk is higher on deeper skin tones and on recently tanned skin. Any procedure that breaks the skin can bleed, become infected and leave a scar; on the chest, the shoulders and the jawline, scars are more likely to thicken. Several of the medicines used in this speciality require blood tests, and some cannot be taken during pregnancy. We tell you your own risk rather than the average one, and where the honest answer is that a condition is better left alone, that is the advice you will get.
Nothing is diagnosed from a photograph. We do not diagnose skin from photographs, and we do not answer "what is this?" by email, by message or through a form. This is not caution for its own sake. A photograph has no history attached to it, cannot be felt, cannot be stretched or pressed to see whether the colour blanches, cannot be examined under a dermatoscope, and misreports colour badly — which matters enormously on skin that is not pale. The examination that actually distinguishes a harmless growth from an early cancer involves magnification, cross-polarised light and, when there is any doubt at all, a biopsy. An application that offers to tell you whether a mole is dangerous from a picture taken on a telephone is selling reassurance, and reassurance is the one product in this field that is dangerous when it is wrong. Bring the mark to a room where somebody can look at it.
Questions
Basal & Squamous Cell Cancer — the questions we are asked most
Is basal cell carcinoma dangerous?
It very rarely spreads to other parts of the body, so in that specific sense it is much less dangerous than melanoma. It is not harmless: it keeps growing where it is, and on a face it destroys the structures it grows into. A small one is a twenty-minute procedure; the same cancer five years later can be a considerably larger operation with a reconstruction attached. That is the whole argument for not waiting.
How long does treatment take?
Most excisions take under an hour from walking into the procedure room to walking out, under local anaesthetic, and you drive yourself home. Recovery is a fortnight of looking after a wound and then several months of a scar settling.
Will it come back?
The one that was removed with clear margins usually does not. What is likely is a different one somewhere else, because the same sun exposure affected all of your skin rather than one square centimetre of it. That is why follow-up examines all of you.
Can it be treated without surgery?
Sometimes. Certain very superficial basal cell cancers respond to a prescription cream used for several weeks, and radiotherapy is an option in particular circumstances. Neither is a general substitute for removing it, and the cream is not appropriate for anything thick, recurrent or on a high-risk site — the honest description is that it is a good option for a minority.
I have a sore that keeps nearly healing. Is that reassuring?
It is the opposite of reassuring, and it is the single sentence most often said by people who turn out to have one of these. Repeated near-healing followed by breaking down again is characteristic. Three weeks without healing is the point at which to book.
Does darker skin get these?
Yes, less often, and squamous cell is proportionally more common than basal cell on deeply pigmented skin — including in sites without much sun exposure, and sometimes arising in long-standing scars or chronic wounds. Being lower risk is not the same as being excluded, and the delay in diagnosis is what does the damage.
Related
Often seen alongside this

Skin Cancer & Lesions
Skin Cancer Screening
A full-body skin examination in good light with a dermatoscope, taking about forty-five minutes. It finds most of what is present on the day it is done — not all of it — and the part that matters as much as the appointment is what you do between appointments.
Read more
Skin Cancer & Lesions
Mole & Lesion Evaluation
One mark, examined properly: history, naked eye, then dermoscopy. Most moles are entirely ordinary and are left alone with reasons given. Anything genuinely uncertain is sampled rather than watched for a year.
Read more
Skin Cancer & Lesions
Melanoma
The least common of the major skin cancers and the one that matters most, because it can spread. Found early it is usually dealt with by removing it. This page is about recognising change and getting seen — not about self-diagnosis.
Read moreA named diagnosis and a written plan you leave holding
Book an appointment
Pick a physician and a time from the calendar — it shows only the hours each of them genuinely has free. A new patient appointment is thirty minutes, a full skin examination forty-five, and you leave with a named diagnosis written down. If something on your skin has changed, telephone instead and say that word: it is triaged differently.