
Some things should not wait for the next free routine appointment. Some things should not wait for the next free routine appointment. Telephone the practice and say what is happening, or go to an emergency room, if you have a mole or a mark that has changed shape, colour or size, that has become raised or uneven, or that bleeds, itches or will not heal; a sore anywhere that has not healed in three weeks; a rash that is spreading quickly, especially with fever, blistering, or peeling skin; a painful rash in a band on one side of the body, particularly near an eye; redness that is hot, swollen, tender and spreading, which can be a deep skin infection; a new rash after starting a medicine, especially with mouth or eye involvement; or a child under three months with any widespread rash. If you have been treated here and something is worse rather than better after a procedure, telephone us rather than waiting for the review appointment. We would far rather field a call that turns out to be nothing.
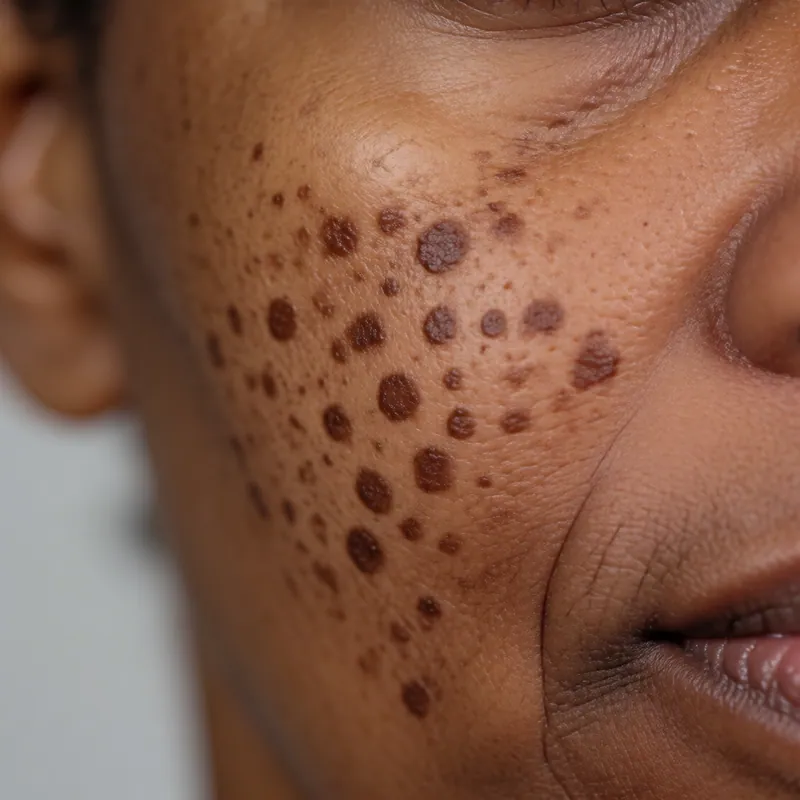
When skin is inflamed — by acne, eczema, an insect bite, a burn, an ingrown hair or an injury — the pigment cells respond by producing extra pigment at that spot. The result is a flat mark: brown or grey-brown when the pigment sits in the upper layers, and grey or blue-grey where inflammation has pushed it deeper. It is not a scar, because no tissue has been lost or gained, and that distinction determines everything about what happens next.
This is the single commonest reason people with deeper skin tones consult a dermatologist, and it is routinely under-treated because it is regarded as cosmetic. Two responses to that. First, whether something matters is not decided by whether it is medically dangerous — a face covered in marks affects how somebody moves through their day. Second, much of it genuinely is medical: the marks are a consequence of an inflammatory disease, and treating that disease properly is the most effective thing anybody can do about them.
The honest timescale is slow. Superficial pigmentation fades over roughly six to twelve months on its own; deeper grey-blue pigmentation can take considerably longer and does not always resolve completely. Treatment shortens that, and nothing available shortens it dramatically. Anybody promising to remove these marks in a few weeks is either selling something or is about to cause more of them.
Getting the order right
This is the part that decides whether the money spent achieves anything.
Treat what is causing the inflammation, first
Every new spot, every eczema flare, every scratched bite produces a new mark. Treating pigmentation while the underlying condition is active is replacing marks at roughly the rate they are being removed. Get the acne, the eczema or the folliculitis controlled, then start on what is left.
Stop the picking and the scratching
Mechanical trauma is inflammation, and it is the one input entirely within your control. Squeezing an inflamed spot deepens and widens the inflammation, which makes both the mark and the risk of a true scar substantially worse.
Daily sun protection, which is not optional here
Ultraviolet exposure darkens existing marks and prolongs them, and it is the single largest factor under your control after the cause itself. Broad spectrum, at least SPF 30, every morning, all year. Tinted mineral sunscreens containing iron oxide additionally block visible light, which genuinely matters for pigmentation on darker skin, where visible light — not only ultraviolet — drives it.
Then treat the pigment, gently
And gently is the operative word. Aggressive treatment on skin prone to pigmentation causes inflammation, which causes pigmentation. More than one patient here has arrived with marks caused entirely by the treatment of the previous marks.
What actually helps the marks
In roughly the order they are tried, with honest expectations attached.
Sun protection, daily, without exception
Named twice deliberately, because it does more than any prescription on this list and costs the least.
Topical pigment-reducing agents
Several ingredients reduce pigment production, of varying strength and available on prescription or over a counter. The strongest is used in courses of a few months rather than indefinitely, because long uninterrupted use carries its own risk of a paradoxical darkening that is difficult to treat. Milder alternatives suit long-term use. Improvement is visible at about three months.
Topical retinoids
Speed up cell turnover, which helps pigment clear faster, and treat acne at the same time where that is the cause. They irritate at first, and on skin prone to pigmentation irritation is not a neutral cost — so introduce slowly, twice weekly, building up.
Chemical peels, carefully chosen
Superficial peels at appropriate strength can speed clearance meaningfully. The choice of agent and strength changes with skin tone, and a peel that is too aggressive on skin prone to pigmentation causes exactly what it was meant to treat. Done here in a series, starting conservatively.
Time, which is the ingredient nobody wants
Six to twelve months for superficial pigmentation, longer for deeper grey-blue pigment. Treatment shortens this; nothing eliminates it. Being told this at the start is what stops people abandoning a plan in month three, which is roughly when it starts to work.
Laser, which is a limited and cautious option
For selected resistant pigmentation, in careful hands, at conservative settings. On deeper skin tones the risk of causing further pigmentation or a pale patch is real, and it is not a first-line treatment for this. Anybody offering aggressive laser for pigmentation on brown skin without discussing that risk should be treated with suspicion.
Telling a mark from a scar
Different problems, different treatments, and confusing them wastes both money and hope.
Flat and coloured — that is a mark, and it fades
Run a finger over it with your eyes closed. If the surface is level with the skin around it and the only difference is colour, it is pigmentation and it will fade with time and treatment.
Dented or raised — that is a scar, and it does not
A texture change means tissue has been lost or gained. No cream affects that. Scars are improved by procedures — see /scar-and-keloid-treatment.html — and improved is the honest word rather than removed.
Red or purple rather than brown
Usually the residual dilated vessels after inflammation rather than pigment. It fades too, often over a similar timescale, and responds to different treatment where it persists.
Both at once, frequently
Acne commonly leaves both a dent and a dark mark at the same site. The mark fades and reveals the scar underneath, which people sometimes experience as getting worse when it is actually the pigmentation clearing.
Marks After Inflammation in western Queens
The brown, grey or purple marks left behind by acne, eczema, an injury or an insect bite. They are not scars and they do fade — slowly, over six to eighteen months, and far faster with daily sun protection than with anything else.
Every appointment here starts the same way: a proper history, an examination in good light, and a named diagnosis said out loud and written down for you to take home. If there is genuine doubt you will be told that, and told what would settle it — usually a biopsy. You leave with a plan that has a strength, a site, a frequency and a date to stop or come back on it, and, where the condition is one that relapses, what to do on the first day of the next flare. If the honest answer is that this is better left alone, or that it belongs somewhere other than here, that is what you get instead, and it costs exactly the same.

This page is not medical advice, and it is not a diagnosis. Nothing on this website is medical advice for you in particular, and it is not a diagnosis. These pages describe conditions in general terms so that you arrive knowing what the questions are — they cannot tell you which condition you have, because that requires somebody to look at your skin, feel it, ask you a hundred questions and frequently take a sample of it. Two conditions on this website can look identical in a photograph and need opposite treatments. If something on your skin is new, changing, painful or not healing, the useful next step is an appointment rather than more reading.
No before-and-after photographs, and no promised outcome. There are no before-and-after photographs on this website and there never will be. Every set you have seen somewhere else was chosen from a much larger pile, and the second picture is usually taken in different light, at a different angle, at a different point in a flare cycle. In dermatology the dishonesty is sharper than in most fields, because nearly every condition here fluctuates on its own — photograph any relapsing skin disease at its worst and again at its best and you have a persuasive pair of images that demonstrates nothing about the treatment in between. What we publish instead is what a treatment typically achieves, in how long, in what proportion of people, and how often it does not work.
The risks, plainly. Every treatment described here has side effects, and some carry real risks. Topical steroids thin skin if they are used at the wrong strength on the wrong site for too long, which is why they are prescribed with a site, a strength and a stopping point rather than handed over indefinitely. Light-based and laser treatment can burn, blister and cause pigment change that lasts months, and that risk is higher on deeper skin tones and on recently tanned skin. Any procedure that breaks the skin can bleed, become infected and leave a scar; on the chest, the shoulders and the jawline, scars are more likely to thicken. Several of the medicines used in this speciality require blood tests, and some cannot be taken during pregnancy. We tell you your own risk rather than the average one, and where the honest answer is that a condition is better left alone, that is the advice you will get.
Nothing is diagnosed from a photograph. We do not diagnose skin from photographs, and we do not answer "what is this?" by email, by message or through a form. This is not caution for its own sake. A photograph has no history attached to it, cannot be felt, cannot be stretched or pressed to see whether the colour blanches, cannot be examined under a dermatoscope, and misreports colour badly — which matters enormously on skin that is not pale. The examination that actually distinguishes a harmless growth from an early cancer involves magnification, cross-polarised light and, when there is any doubt at all, a biopsy. An application that offers to tell you whether a mole is dangerous from a picture taken on a telephone is selling reassurance, and reassurance is the one product in this field that is dangerous when it is wrong. Bring the mark to a room where somebody can look at it.
Questions
Marks After Inflammation — the questions we are asked most
How long will these marks take to fade?
Roughly six to twelve months for the brown, superficial kind, and longer for the grey-blue kind where pigment has settled deeper — that variety sometimes does not clear completely. Treatment shortens it and nothing eliminates it. Knowing that at the start is what allows people to stay with a plan through month three, which is when it begins to show.
Is this a scar?
If it is flat and the only difference is colour, no — it is pigmentation and it fades. If you can feel a dent or a raised area, that is a scar, and creams do not affect it. It is worth checking with your eyes closed and a fingertip, because the two are frequently confused and they need entirely different treatment.
Why is this so much worse on my skin than on my friend's?
Because more active pigment cells respond more vigorously to inflammation. Deeper skin tones develop post-inflammatory pigmentation more readily, more visibly and for longer. It also means treatment has to be gentler, because irritation itself causes pigmentation — which is why an aggressive approach that works on pale skin is the wrong approach here.
Can I use a skin-lightening product from a shop?
Be careful. Products sold outside regulated channels, including some marketed for this specific purpose, have been found to contain mercury or potent steroids, both of which cause serious harm — steroids in particular thin the skin and cause a rebound darkening worse than the original. If you are using something bought abroad or online, bring the actual container to the appointment.
Should I have laser treatment for these?
Usually not as a first approach, and on deeper skin tones the risk of causing further pigmentation or a pale patch is genuine. Topical treatment, careful superficial peels, sun protection and time do most of the work with far less risk. Laser has a role for selected resistant cases at conservative settings, and anybody proposing it aggressively without discussing that risk is not being straight with you.
My acne is under control but the marks are still there. Is the treatment failing?
No — that is the expected sequence. The marks outlast the acne by many months, because they are the record of inflammation that has already happened rather than evidence of inflammation continuing. This is the point at which treating the pigmentation itself becomes worthwhile, because there is nothing actively producing new marks.
Related
Often seen alongside this

Pigment & Skin Tone
Melasma
Symmetrical brown patches across the cheeks, forehead and upper lip, driven by hormones and light. It is the most stubborn pigmentation in dermatology, it relapses reliably, and daily sun protection is not advice here — it is the treatment.
Read more
Pigment & Skin Tone
Vitiligo
An autoimmune condition in which pigment cells are lost, producing well-defined pale patches. It is not contagious, it is not caused by diet, and treatment has genuinely improved — repigmentation is possible, slow, and better at some sites than others.
Read more
Pigment & Skin Tone
Skin of Color Dermatology
Not a separate speciality — a set of things that are genuinely different and that this field's defaults were not built around. Redness reads differently, pigment change is the presenting complaint more often than the disease, and every light-based treatment carries different risk.
Read moreA named diagnosis and a written plan you leave holding
Book an appointment
Pick a physician and a time from the calendar — it shows only the hours each of them genuinely has free. A new patient appointment is thirty minutes, a full skin examination forty-five, and you leave with a named diagnosis written down. If something on your skin has changed, telephone instead and say that word: it is triaged differently.