Some things should not wait for the next free routine appointment. Some things should not wait for the next free routine appointment. Telephone the practice and say what is happening, or go to an emergency room, if you have a mole or a mark that has changed shape, colour or size, that has become raised or uneven, or that bleeds, itches or will not heal; a sore anywhere that has not healed in three weeks; a rash that is spreading quickly, especially with fever, blistering, or peeling skin; a painful rash in a band on one side of the body, particularly near an eye; redness that is hot, swollen, tender and spreading, which can be a deep skin infection; a new rash after starting a medicine, especially with mouth or eye involvement; or a child under three months with any widespread rash. If you have been treated here and something is worse rather than better after a procedure, telephone us rather than waiting for the review appointment. We would far rather field a call that turns out to be nothing.
Eczema is a barrier problem and an immune problem at once. The skin does not hold water well, which lets irritants and allergens in, which provokes inflammation, which damages the barrier further. That loop is why treatment has two halves that both matter: repairing and protecting the barrier every single day, and damping the inflammation when it flares. People who do only the second get better and then relapse; people who do only the first never get comfortable in the first place.
The single commonest treatment failure this practice sees is not overuse of steroids — it is the opposite. Somebody is given a weak preparation, uses it for three days on skin that needed two weeks of something stronger, decides it does not work, and repeats that cycle for years while the disease stays active. Chronically inflamed skin thins and scars too. The fear is understandable and it was taught by people acting in good faith, but the honest position is that under-treatment causes more harm here than over-treatment, and both are avoidable by writing down a strength, a site, a frequency and a stopping point.
It is also worth naming what eczema costs, because it gets discussed as a rash. It wakes people every night, and broken sleep makes the itch worse and the following day harder. It keeps children out of school and adults off work. It changes what people wear and whether they swim. Treating it as a serious condition rather than a cosmetic nuisance is the difference between a plan that works and a tube handed over at a door.
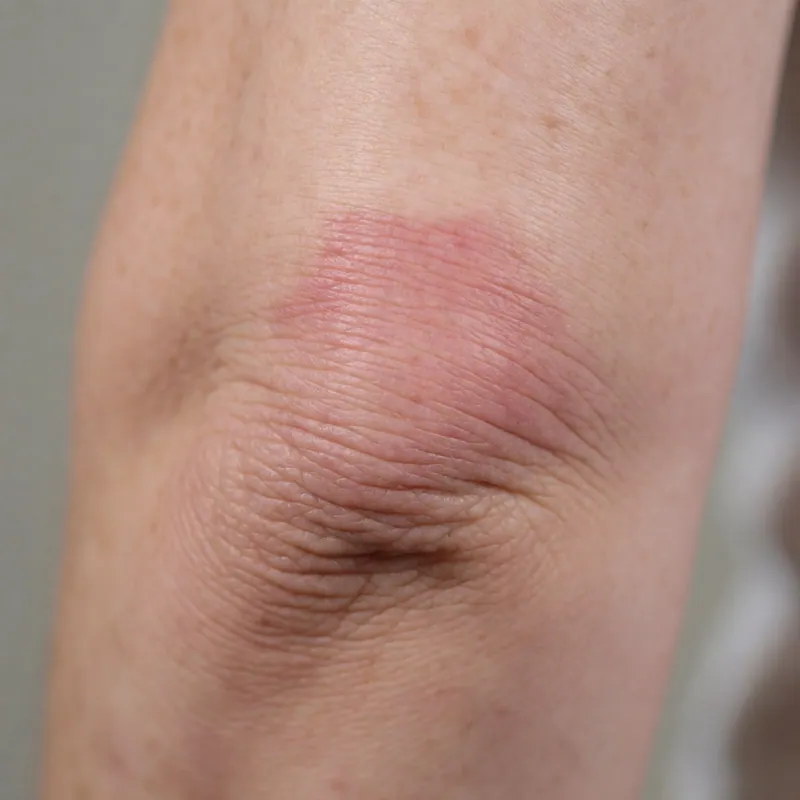
The daily half — barrier care
Unglamorous, entirely effective, and where most of the benefit actually comes from.
Far more moisturiser than you think
An adult with widespread eczema needs roughly 500 grams a week. Almost nobody uses a tenth of that. If a tub lasts you two months, the quantity is the problem before the product is. Apply it in the direction the hair grows, do not rub it in vigorously, and reapply whenever skin feels tight.
Thicker is better on drier skin
Ointments hold water better than creams and creams better than lotions. The trade-off is greasiness, so a common plan is an ointment overnight and a cream during the day. If a product stings, that is information — it usually means the barrier is broken enough to feel the preservatives, and it sometimes means an allergy.
Within three minutes of a shower
Short, lukewarm showers rather than long hot ones, pat rather than rub, and moisturise while the skin is still damp. Hot water feels wonderful on itchy skin for ninety seconds and makes the next six hours worse.
Soap is usually the problem in winter
Ordinary soaps and foaming washes strip lipid from a barrier that is already failing. A soap substitute or a non-foaming wash, and no bubble bath for children.
Cotton, short nails, and cool rooms at night
Wool and synthetics next to the skin provoke it, overheated bedrooms make the itch worse, and short nails limit the damage done in the night by scratching nobody is awake for.
The flare half — treating inflammation properly
How topical steroids are actually meant to be used, and why the fear of them causes harm.
A strength matched to the site and the severity
Facial and flexural skin takes a mild preparation; thick skin on palms and soles needs a potent one. Using a mild cream on a thick patch is not the safe option — it is the ineffective one, and the disease stays active for months longer than it needed to.
Enough of it, for long enough
Typically twice a day until the skin is genuinely smooth to the touch rather than merely less red, then stopped or stepped down. Stopping the moment the redness goes is what produces the flare-treat-relapse pattern people describe as the treatment not lasting.
A written stopping point, every time
Every steroid prescribed here leaves with a site, a strength, a frequency and a date to stop or review. That is what makes it safe. Skin thinning comes from potent preparations used on delicate sites for months without review, not from two weeks of correct use.
Weekend maintenance, for skin that keeps flaring in the same place
Applying treatment twice a week to sites that repeatedly flare, on top of daily moisturiser, substantially reduces how often flares happen. This is the step most often missing from a plan that is nearly working.
Steroid-free anti-inflammatory options
For the face, the eyelids and the folds, and for anyone needing long-term control at a delicate site, there are non-steroid prescription creams that damp the same inflammation without the thinning risk. They sting for the first few days in some people and that settles.
Treat the infection when there is one
Weeping, yellow crusting, sudden worsening or painful clustered blisters suggest infection on top of eczema, which needs its own treatment. The blistering, painful, rapidly spreading version is urgent and should not wait for a routine appointment.
When there is more going on
The investigations and the escalations, and when each is genuinely indicated.
Patch testing, where the pattern suggests contact allergy
Eczema confined to the hands, the face, the eyelids or under a watch strap, or eczema that started in adulthood in somebody who never had it as a child, is worth testing. It is the appointment that ends the most long-running dermatitis here, and it distinguishes allergy from irritation — which look identical and need opposite advice. See /patch-testing.html.
Phototherapy, for widespread disease
Narrowband ultraviolet light in a cabinet, two or three times a week for a course of months. Genuinely effective for extensive eczema, avoids systemic medication entirely, and its real cost is the number of visits. See /phototherapy.html.
Systemic treatment, for severe disease
Where eczema is extensive, is not controlled by adequate topical treatment and is affecting sleep, work or school, there are tablets and injectable treatments that suppress the specific immune signals driving it. The newer targeted injectable options are considerably more selective than the older immune-suppressing tablets, and they have changed what is achievable for severe disease. All require monitoring, and none of them is named on this website — that conversation happens in the room.
Allergy testing is not usually the answer for typical childhood eczema
Food allergy testing in a child with ordinary eczema and no history of immediate reactions produces a great many positive results that are not causing the eczema, and leads to unnecessary and occasionally harmful food restriction. Where there is a genuine history of immediate reaction, that is different and is worth investigating.
Rethinking the diagnosis when nothing works
Eczema that is not responding to correct treatment sometimes is not eczema. A stubborn single patch, an asymmetrical rash or one steadily widening at the edge deserves a fresh look and occasionally a biopsy.
Eczema & Dermatitis in western Queens
Itchy, inflamed, dry skin that flares and settles. It is controlled rather than cured, most of it is under-treated rather than over-treated, and the plan you leave with should include what to do on the first day of the next flare.
Every appointment here starts the same way: a proper history, an examination in good light, and a named diagnosis said out loud and written down for you to take home. If there is genuine doubt you will be told that, and told what would settle it — usually a biopsy. You leave with a plan that has a strength, a site, a frequency and a date to stop or come back on it, and, where the condition is one that relapses, what to do on the first day of the next flare. If the honest answer is that this is better left alone, or that it belongs somewhere other than here, that is what you get instead, and it costs exactly the same.

This page is not medical advice, and it is not a diagnosis. Nothing on this website is medical advice for you in particular, and it is not a diagnosis. These pages describe conditions in general terms so that you arrive knowing what the questions are — they cannot tell you which condition you have, because that requires somebody to look at your skin, feel it, ask you a hundred questions and frequently take a sample of it. Two conditions on this website can look identical in a photograph and need opposite treatments. If something on your skin is new, changing, painful or not healing, the useful next step is an appointment rather than more reading.
No before-and-after photographs, and no promised outcome. There are no before-and-after photographs on this website and there never will be. Every set you have seen somewhere else was chosen from a much larger pile, and the second picture is usually taken in different light, at a different angle, at a different point in a flare cycle. In dermatology the dishonesty is sharper than in most fields, because nearly every condition here fluctuates on its own — photograph any relapsing skin disease at its worst and again at its best and you have a persuasive pair of images that demonstrates nothing about the treatment in between. What we publish instead is what a treatment typically achieves, in how long, in what proportion of people, and how often it does not work.
The risks, plainly. Every treatment described here has side effects, and some carry real risks. Topical steroids thin skin if they are used at the wrong strength on the wrong site for too long, which is why they are prescribed with a site, a strength and a stopping point rather than handed over indefinitely. Light-based and laser treatment can burn, blister and cause pigment change that lasts months, and that risk is higher on deeper skin tones and on recently tanned skin. Any procedure that breaks the skin can bleed, become infected and leave a scar; on the chest, the shoulders and the jawline, scars are more likely to thicken. Several of the medicines used in this speciality require blood tests, and some cannot be taken during pregnancy. We tell you your own risk rather than the average one, and where the honest answer is that a condition is better left alone, that is the advice you will get.
Nothing is diagnosed from a photograph. We do not diagnose skin from photographs, and we do not answer "what is this?" by email, by message or through a form. This is not caution for its own sake. A photograph has no history attached to it, cannot be felt, cannot be stretched or pressed to see whether the colour blanches, cannot be examined under a dermatoscope, and misreports colour badly — which matters enormously on skin that is not pale. The examination that actually distinguishes a harmless growth from an early cancer involves magnification, cross-polarised light and, when there is any doubt at all, a biopsy. An application that offers to tell you whether a mole is dangerous from a picture taken on a telephone is selling reassurance, and reassurance is the one product in this field that is dangerous when it is wrong. Bring the mark to a room where somebody can look at it.
Questions
Eczema & Dermatitis — the questions we are asked most
Can eczema be cured?
No. It is controlled rather than cured, and any practice telling you otherwise is being careless with the word. What good treatment achieves is long stretches of comfortable skin, flares that are shorter and milder, and knowing exactly what to do on the first day of one. Many children improve substantially as they grow, which is not the same as a cure and is worth having anyway.
Are steroid creams going to thin my skin?
Used correctly — right strength for the site, for a defined period, with a review — that is not what happens. Thinning comes from potent preparations used on delicate skin for months without anyone checking. The problem we actually see far more often is the opposite: something far too weak, used for three days, abandoned, repeated for years while the disease stays active. Chronically inflamed skin damages too.
How much moisturiser should I really be using?
For an adult with widespread eczema, roughly 500 grams a week. That number surprises everybody. If your tub lasts two months you are using about a tenth of what would help. Quantity and frequency matter more than which product it is.
Is it caused by something I am eating?
Usually not, and food allergy testing in a child with ordinary eczema and no history of immediate reactions tends to produce misleading positives and unnecessary food restriction. Where there is a genuine history of an immediate reaction — swelling, hives, vomiting within minutes — that is a different question and worth investigating.
Should I be patch tested?
Worth considering if your eczema is confined to hands, face or eyelids, if it started in adulthood when you never had it as a child, if it corresponds to where something touches you, or if it has stopped responding to treatment that used to work. It is the appointment that ends the most long-running dermatitis in this practice.
My child scratches all night. What can actually be done tonight?
Adequate treatment of the inflammation is what stops the itch — antihistamines do much less than people expect for eczema itch specifically, though a sedating one occasionally buys a night's sleep. In the meantime: cool the bedroom, cotton nightwear, nails cut right down, generous ointment before bed, and damp wrapping over treated skin if we have shown you how. A child scratching every night is a reason to be seen sooner rather than to persevere.
Why does it keep coming back in exactly the same places?
Because those sites have the most fragile barrier for you, and treating a flare does not change that. This is precisely what maintenance treatment is for: applying something twice a week to the places that repeatedly flare, on top of daily moisturiser, which substantially reduces how often they do.
Related
Often seen alongside this

Inflammatory Skin Disease
Acne
The commonest reason anybody sees a dermatologist. It is treatable in almost everybody, it takes about three months before you can judge whether a treatment worked, and treating it properly is how you avoid the scars.
Read more
Inflammatory Skin Disease
Psoriasis
An immune-driven condition, not a skin infection and not contagious. Treatment ranges from creams through light therapy to targeted injections, and what has become achievable for severe psoriasis in the last decade is genuinely different from what came before.
Read more
Inflammatory Skin Disease
Rosacea
Persistent central facial redness, flushing, visible vessels and inflammatory bumps. It is not acne, it is not caused by drinking, and the single most effective thing most people do for it is daily sun protection.
Read moreA named diagnosis and a written plan you leave holding
Book an appointment
Pick a physician and a time from the calendar — it shows only the hours each of them genuinely has free. A new patient appointment is thirty minutes, a full skin examination forty-five, and you leave with a named diagnosis written down. If something on your skin has changed, telephone instead and say that word: it is triaged differently.