Some things should not wait for the next free routine appointment. Some things should not wait for the next free routine appointment. Telephone the practice and say what is happening, or go to an emergency room, if you have a mole or a mark that has changed shape, colour or size, that has become raised or uneven, or that bleeds, itches or will not heal; a sore anywhere that has not healed in three weeks; a rash that is spreading quickly, especially with fever, blistering, or peeling skin; a painful rash in a band on one side of the body, particularly near an eye; redness that is hot, swollen, tender and spreading, which can be a deep skin infection; a new rash after starting a medicine, especially with mouth or eye involvement; or a child under three months with any widespread rash. If you have been treated here and something is worse rather than better after a procedure, telephone us rather than waiting for the review appointment. We would far rather field a call that turns out to be nothing.
The assessment has three parts and the first is talking. How long has it been there, has it changed, in what way, over what period, does it itch or bleed, has anything been done to it, and is there anything else on you that looks like it. A mark that has been unchanged since childhood and a mark that appeared eight months ago are different problems even when they look identical.
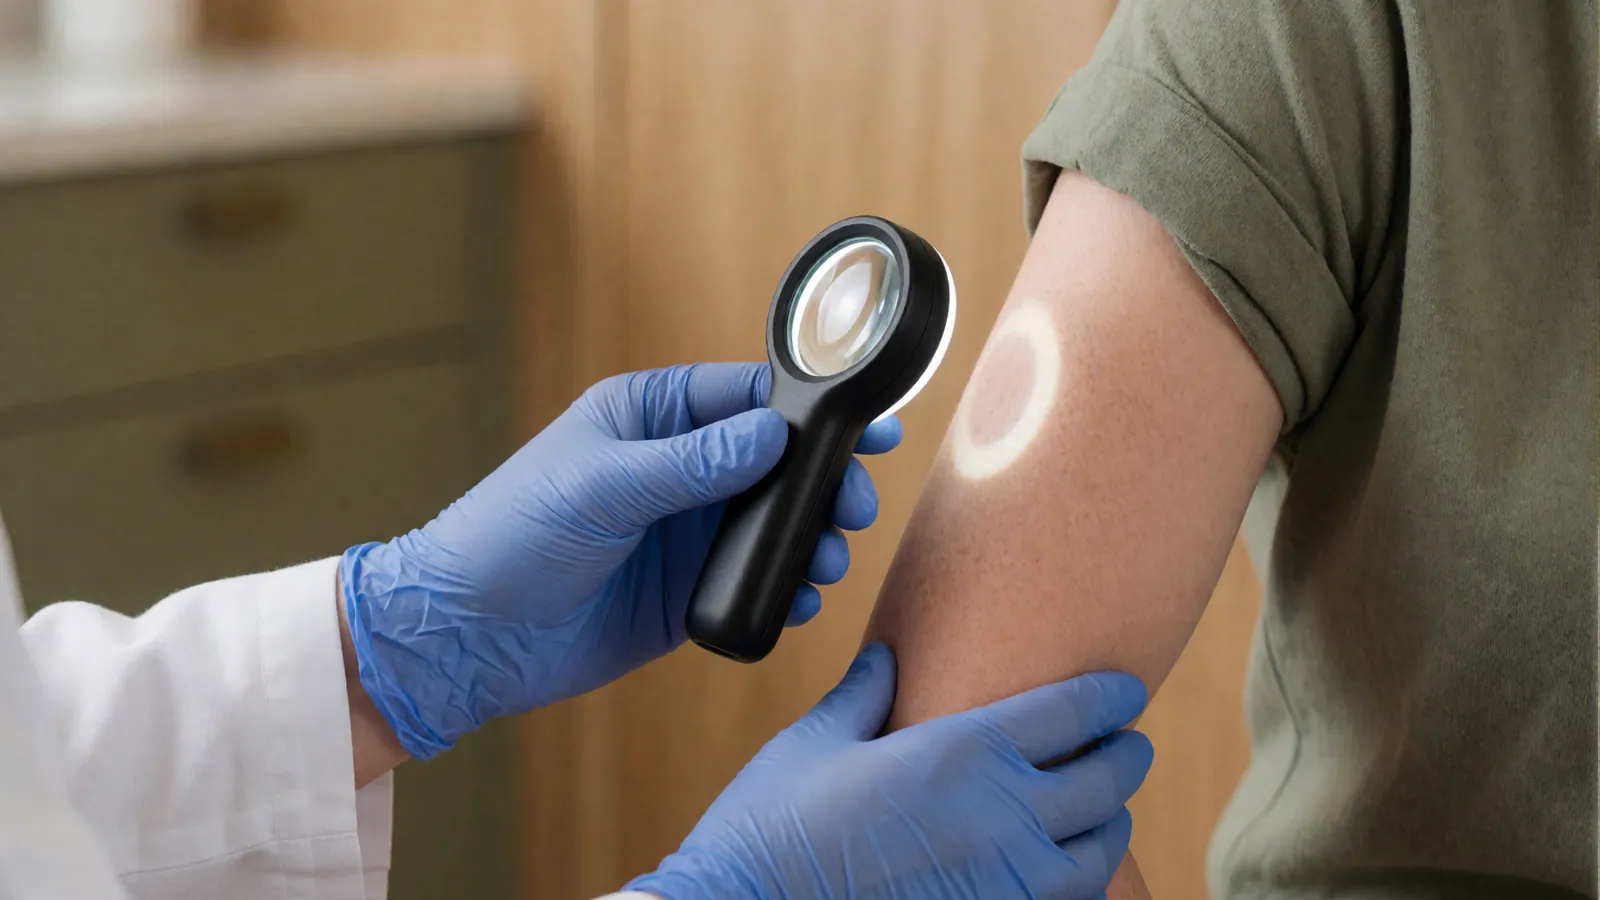
Then the mark is examined by eye in good light, and then through a dermatoscope. Under cross-polarised magnification a mole shows structures that are invisible unaided: the pattern of its pigment network, its vessels, whether the colour is arranged symmetrically. Most of the marks people bring in are entirely ordinary, and dermoscopy is why we can say so with confidence rather than with a shrug — and why we do not have to remove things merely to end the uncertainty.
It is also worth saying plainly that many of the things people arrive worried about are not moles at all. A large share turn out to be the warty brown growths that almost everybody develops from middle age onwards, or a harmless small red spot, or a scar. Being told what something is, by name, is usually the whole of the treatment.
What we are actually looking at
The features that raise suspicion, and why the popular checklist is a starting point rather than an answer.
Asymmetry, border, colour, diameter, evolving
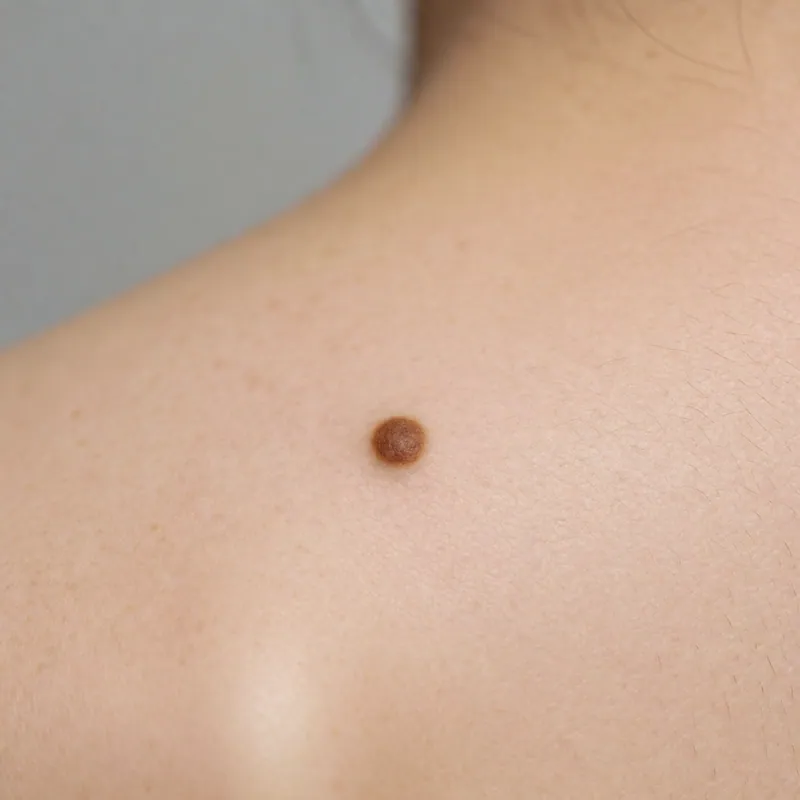
The familiar checklist, and a genuinely useful one for the public: a mole where one half does not match the other, with a ragged or blurred outline, with more than one colour in it, larger than about six millimetres, or changing in any respect. If a mark of yours does several of those things, book.
What that checklist misses
Nodular melanoma, which is the fast one. It is often symmetrical, evenly coloured, small, and sometimes pink or red rather than brown — it fails every letter of the checklist. What it does instead is grow, and feel firm, and sometimes bleed. Anything raised that has appeared recently and is getting bigger deserves an appointment regardless of how tidy it looks.
The odd one out
Your moles mostly resemble each other. The one that does not follow your own pattern is worth more attention than any absolute rule about size or colour, and it is a much easier thing for a patient to notice than a millimetre measurement.
A sore that has not healed
Three weeks is the threshold. A patch that scabs, comes off, bleeds a little and scabs again for months is one of the commonest presentations of the commonest skin cancer, and people routinely put it down to a scratch or a shaving cut for a year.
Under the nails, on the palms and on the soles
A dark band running the length of a nail, particularly a single one, particularly if it is widening or if the pigment spills onto the skin at the base. These sites matter most on darker skin and are the ones most often missed.
Why we leave most moles alone
Removing everything is not the safe option people assume it is.
The ordinary ones are not going to become cancers
A common mole that has looked the same for twenty years is a common mole. Removing it achieves nothing except a scar, and a fair number of people arrive expecting that a thorough practice removes moles routinely. A thorough practice examines them and explains why they can stay.
Every removal leaves a mark
On the chest, the shoulders, the upper back and the jawline, scars are more likely to thicken and can end up considerably more noticeable than what was removed. That is a real cost, and it belongs in the conversation before the procedure rather than after it.
Cosmetic removal is a different conversation, and it is honest to have it
If a mole catches on a collar, is nicked shaving, or you simply dislike it, that is a reasonable reason to remove it. It is cosmetic rather than medical, it is priced accordingly and insurance generally will not cover it, and you will be told all of that before it happens. Anything removed here is sent for examination regardless of why it was removed.
What we will not do is monitor something that should be sampled
Watching a suspicious mark for six months is a decision with a cost, and the cost falls entirely on the patient. Where there is genuine doubt, the answer is a biopsy now. We would far rather remove ten harmless things than watch one that mattered, and that ratio is the honest price of finding cancers early.
The things people most often bring in
And what they usually turn out to be. None of this is a diagnosis of anything on you.
Warty, stuck-on brown growths
Extremely common from middle age, often multiple, often on the trunk, and entirely harmless. They look as though they have been dropped onto the skin rather than grown out of it. They can be removed if they catch or you dislike them, which is cosmetic.
Small bright red dots
Tiny collections of blood vessels, harmless, increasingly common with age, and not related to anything serious. They can bleed impressively if caught, which is what usually brings them in.
A firm pale lump under the skin
Frequently a cyst or a fatty lump, both harmless, both removable if they are uncomfortable or growing. See /cyst-and-lipoma-removal.html.
A rough scaly patch that keeps coming back
Often sun damage rather than a growth — see /actinic-keratosis.html. These are worth treating because a small proportion progress, which makes it one of the few genuinely preventive treatments here.
A pearly bump with visible vessels that bleeds
This is the description that gets the soonest appointment, because it is the classic presentation of the commonest skin cancer. It is also very treatable when it is small, which is the entire argument for coming in early rather than waiting.
Mole & Lesion Evaluation in western Queens
One mark, examined properly: history, naked eye, then dermoscopy. Most moles are entirely ordinary and are left alone with reasons given. Anything genuinely uncertain is sampled rather than watched for a year.
Every appointment here starts the same way: a proper history, an examination in good light, and a named diagnosis said out loud and written down for you to take home. If there is genuine doubt you will be told that, and told what would settle it — usually a biopsy. You leave with a plan that has a strength, a site, a frequency and a date to stop or come back on it, and, where the condition is one that relapses, what to do on the first day of the next flare. If the honest answer is that this is better left alone, or that it belongs somewhere other than here, that is what you get instead, and it costs exactly the same.

This page is not medical advice, and it is not a diagnosis. Nothing on this website is medical advice for you in particular, and it is not a diagnosis. These pages describe conditions in general terms so that you arrive knowing what the questions are — they cannot tell you which condition you have, because that requires somebody to look at your skin, feel it, ask you a hundred questions and frequently take a sample of it. Two conditions on this website can look identical in a photograph and need opposite treatments. If something on your skin is new, changing, painful or not healing, the useful next step is an appointment rather than more reading.
No before-and-after photographs, and no promised outcome. There are no before-and-after photographs on this website and there never will be. Every set you have seen somewhere else was chosen from a much larger pile, and the second picture is usually taken in different light, at a different angle, at a different point in a flare cycle. In dermatology the dishonesty is sharper than in most fields, because nearly every condition here fluctuates on its own — photograph any relapsing skin disease at its worst and again at its best and you have a persuasive pair of images that demonstrates nothing about the treatment in between. What we publish instead is what a treatment typically achieves, in how long, in what proportion of people, and how often it does not work.
The risks, plainly. Every treatment described here has side effects, and some carry real risks. Topical steroids thin skin if they are used at the wrong strength on the wrong site for too long, which is why they are prescribed with a site, a strength and a stopping point rather than handed over indefinitely. Light-based and laser treatment can burn, blister and cause pigment change that lasts months, and that risk is higher on deeper skin tones and on recently tanned skin. Any procedure that breaks the skin can bleed, become infected and leave a scar; on the chest, the shoulders and the jawline, scars are more likely to thicken. Several of the medicines used in this speciality require blood tests, and some cannot be taken during pregnancy. We tell you your own risk rather than the average one, and where the honest answer is that a condition is better left alone, that is the advice you will get.
Nothing is diagnosed from a photograph. We do not diagnose skin from photographs, and we do not answer "what is this?" by email, by message or through a form. This is not caution for its own sake. A photograph has no history attached to it, cannot be felt, cannot be stretched or pressed to see whether the colour blanches, cannot be examined under a dermatoscope, and misreports colour badly — which matters enormously on skin that is not pale. The examination that actually distinguishes a harmless growth from an early cancer involves magnification, cross-polarised light and, when there is any doubt at all, a biopsy. An application that offers to tell you whether a mole is dangerous from a picture taken on a telephone is selling reassurance, and reassurance is the one product in this field that is dangerous when it is wrong. Bring the mark to a room where somebody can look at it.
Questions
Mole & Lesion Evaluation — the questions we are asked most
Can I send a photograph first, just to see whether it is worth an appointment?
No. We do not assess photographs, and the reason is not caution for its own sake: a photograph has no history attached, cannot be felt, cannot be dermoscoped and misreports colour, and the marks that are most dangerous are frequently the least dramatic to look at. Being told by email that a picture looks fine is worse than being told nothing, because it stops you booking. /no-diagnosis-online.html sets out the full reasoning.
Will you remove it at the same appointment?
Often yes, if it needs removing and the diagnosis is clear enough to choose the right technique. Anything possibly a melanoma is taken whole with a margin rather than shaved, and that is planned rather than improvised, so occasionally it means a second short appointment.
Does a mole that is removed grow back?
A shaved mole can regrow pigment at the site, which is one reason a shave is the wrong technique for anything uncertain — regrown pigment in a scar is difficult to interpret afterwards. A mole taken out fully with sutures does not come back.
I have a lot of moles. Is that itself a problem?
It raises your risk, which changes how often you should be examined rather than meaning anything is wrong. People with many moles benefit most from a mapped baseline examination and from monthly self-checks, because their signal is the mark that breaks their own pattern.
It itches. Does that mean it is cancer?
It means it is worth looking at. Itch is on the list of changes that matter, along with bleeding, crusting and growth — but far more itchy marks are irritated by clothing than are cancers. That is exactly the sort of question a fifteen-minute appointment answers and a website cannot.
What if you are not sure?
You will be told that we are not sure, which is a more useful sentence than a confident guess. Genuine uncertainty is settled by sampling it, not by monitoring it, unless there is a specific reason to wait — and if there is, you will be told what that reason is and exactly what would bring you back sooner.
Related
Often seen alongside this

Skin Cancer & Lesions
Skin Cancer Screening
A full-body skin examination in good light with a dermatoscope, taking about forty-five minutes. It finds most of what is present on the day it is done — not all of it — and the part that matters as much as the appointment is what you do between appointments.
Read more
Skin Cancer & Lesions
Melanoma
The least common of the major skin cancers and the one that matters most, because it can spread. Found early it is usually dealt with by removing it. This page is about recognising change and getting seen — not about self-diagnosis.
Read more
Skin Cancer & Lesions
Basal & Squamous Cell Cancer
The two common skin cancers. Both are usually slow, both are usually cured by removing them, and both are routinely ignored for a year because they look like a sore that will not heal. Most are treated in this building.
Read moreA named diagnosis and a written plan you leave holding
Book an appointment
Pick a physician and a time from the calendar — it shows only the hours each of them genuinely has free. A new patient appointment is thirty minutes, a full skin examination forty-five, and you leave with a named diagnosis written down. If something on your skin has changed, telephone instead and say that word: it is triaged differently.